
Cardiogenic shock
When the heart can't keep up
A heart attack or failing heart muscle can drop blood flow below what the body needs to survive. Swipe to see how New Mexico responds.

New Mexico Cardiogenic Shock Network
Building a statewide system of care so every New Mexican in cardiogenic shock has equal access to life-saving treatment — regardless of which emergency room they enter.
Start here
NMCSN is built to guide anyone touched by cardiogenic shock — comprehensive care, from first suspicion to recovery.
Pick one to get started.
Suspected cardiogenic shock?
Three taps tell you whether to call.
You do not need a confirmed diagnosis. Currently routes to Heart Hospital of New Mexico; UNM coming soon.
A heart attack or failing heart muscle can drop blood flow below what the body needs to survive. Swipe to see how New Mexico responds.
In cardiogenic shock the heart can't move enough blood. Without that flow, the kidneys, liver and brain begin to fail. Early, coordinated care changes what happens next.
Shock often looks like sepsis, kidney failure, or a patient who just looks unwell. By the time the cause is clear, valuable time can be gone.
Referring clinicians can activate the network for a patient in shock even when the cause is still unknown. The team on the other end helps sort it out.
Cardiology, cardiac surgery, critical care and heart failure specialists review the case together and choose the support that fits.
2026 ESC Heart Failure Guidelines: multidisciplinary shock team, Class I (Level of Evidence C). Køber et al., Eur Heart J 2026Working to connect hospitals across New Mexico to one shock team, so the right care can reach a patient wherever they start.
Our Mission
No matter where they live or receive care in New Mexico and the surrounding region, every patient deserves the same chance to survive cardiogenic shock.
We coordinate rapid identification, stabilization, and transfer through standardized protocols, AI-enabled tools, and a hub-and-spoke network we are building to link rural hospitals and EMS to high-capability shock centers.
Build cardiac trauma systems around people, not devices.
Early recognition through standardized triage protocols and hemo-metabolic triggers, with the goal of reaching every ER in the state.
Coordinated transport pathways connecting spoke hospitals to hub shock centers with one-call activation.
Phenotype-guided mechanical circulatory support, hemodynamic monitoring, and shock team protocols.
The Problem
of patients with cardiogenic shock die despite modern therapy — 30-day mortality was 47–56% in the SHOCK trial and remained 40% in IABP-SHOCK II thirteen years later.1,2
higher in-hospital mortality at hospitals without PCI capability (64.4%) than at transplant and LVAD centers (36.5%) — in 1.17 million US shock hospitalizations. Hospital capability is strongly tied to survival.3
average transfer distance to definitive shock care in New Mexico, and up to 320 miles. We receive patients from across New Mexico — distances that decide who reaches a shock team at all.
Coordinated shock care is associated with substantially higher survival. One program’s 30-day survival rose from 47% to 76.6% over two years after adding a multidisciplinary shock team;5 centers with shock teams report lower ICU mortality than those without (23% vs 29%);6 and a national single-arm, protocol-driven initiative reported 71% survival to discharge in AMI-related shock.7 NMCSN is building this for New Mexico.
Our Protocols
How our shock team identifies, calls, and manages cardiogenic shock — shared openly so any clinician at any hospital can use them. Click a protocol to view it full size.
or
If POCUS suggests distributive or hypovolemic shock → follow sepsis/other pathway, no shock call
Shock call
Multidisciplinary Shock Team Consultation
Level 1 Hub Transfer: 1-888-727-7646
Shock Team Activation Algorithm · Version 2.0, February 2026 · Full figure
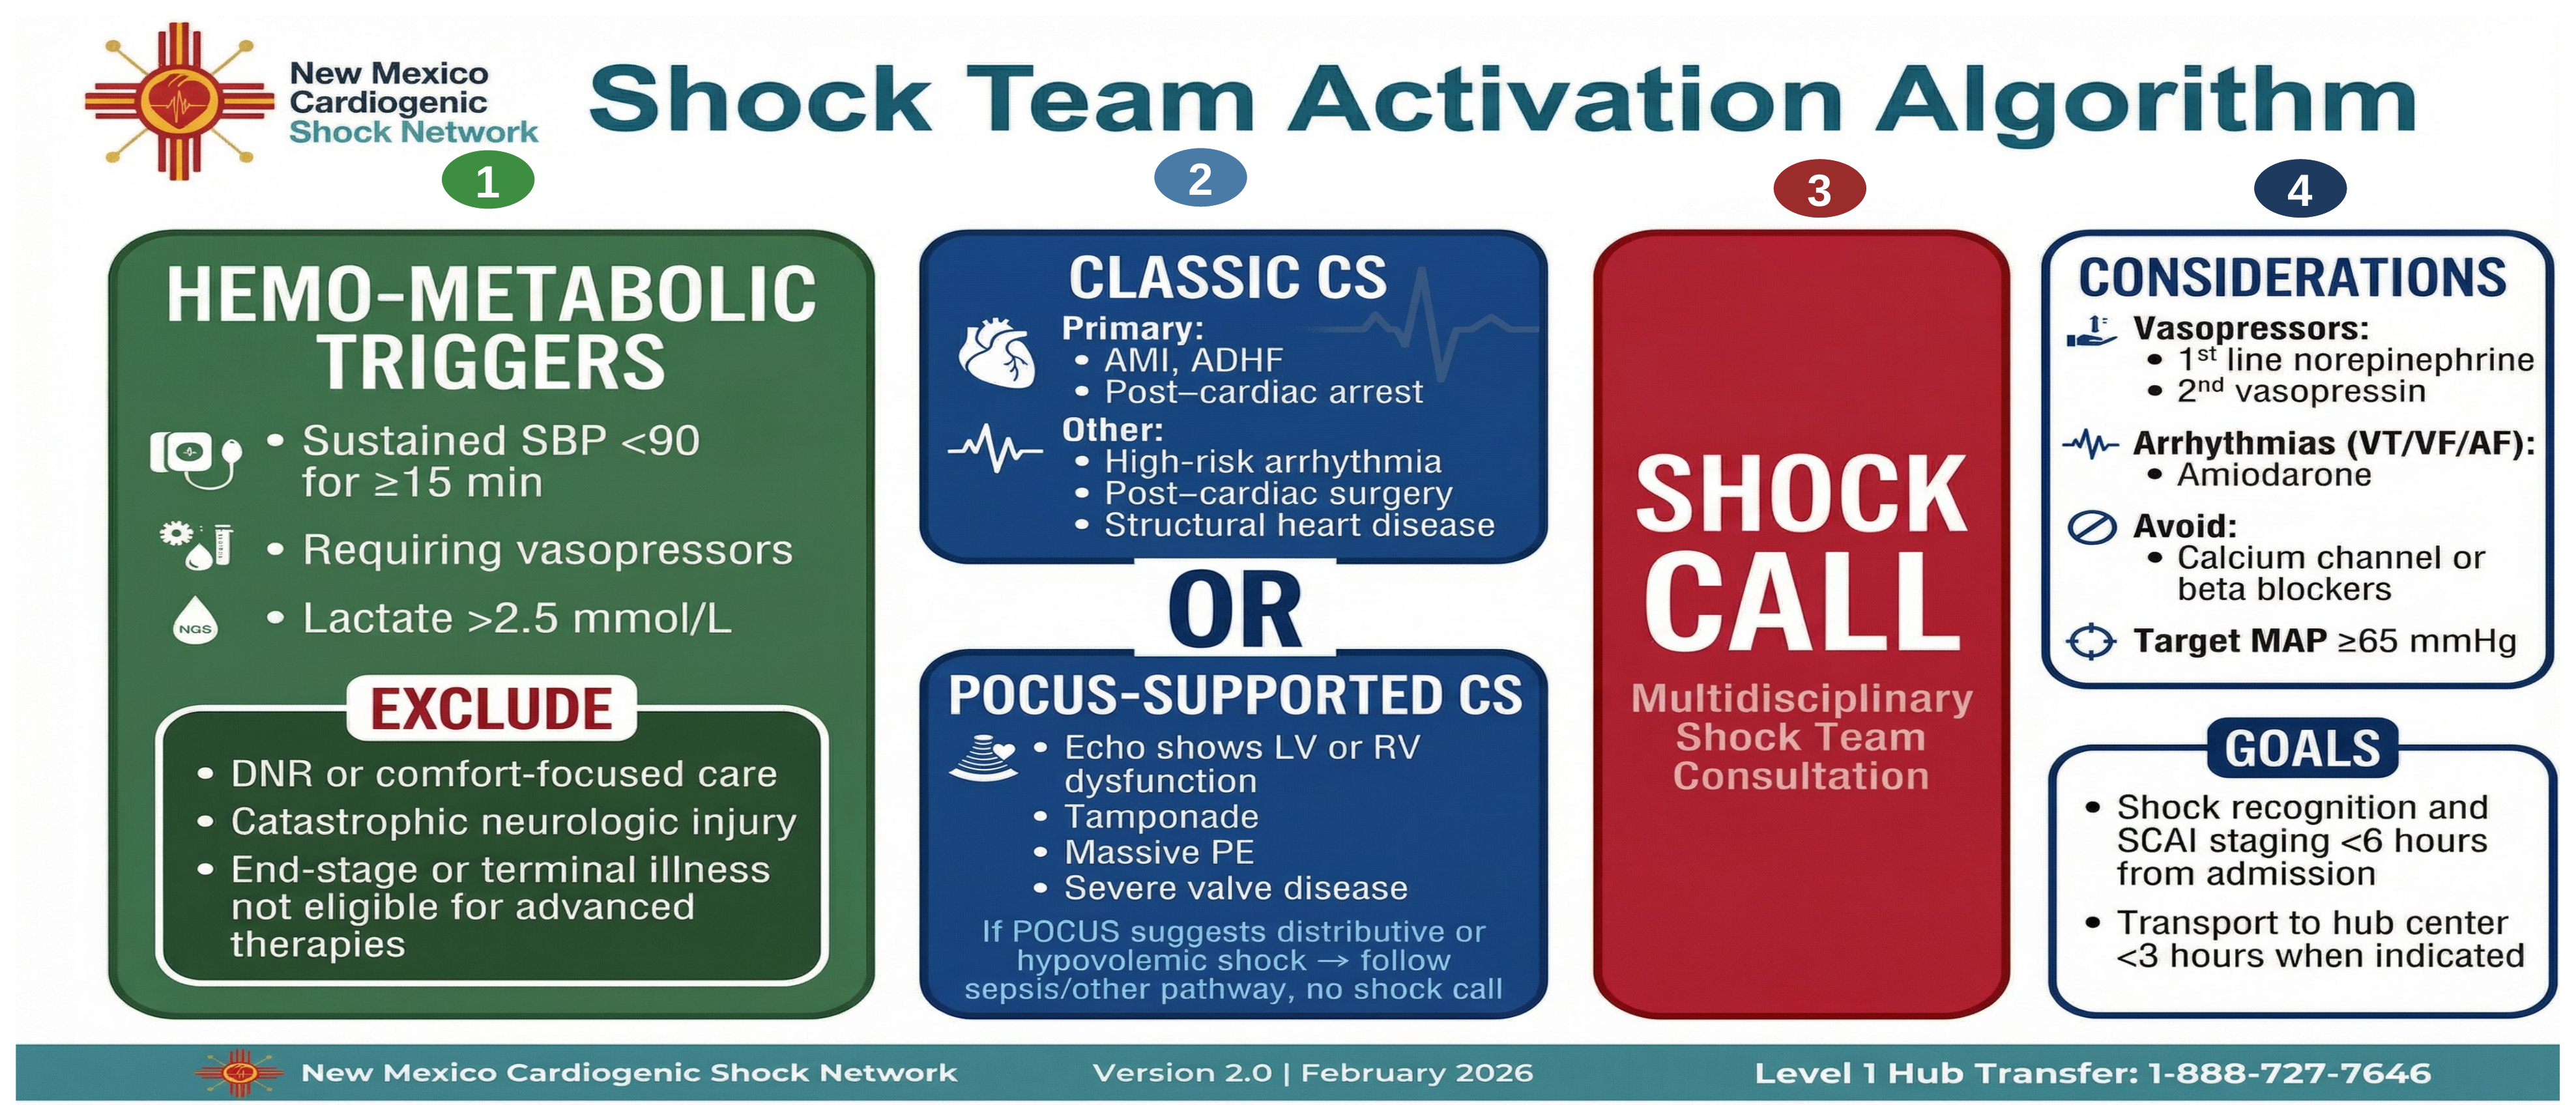
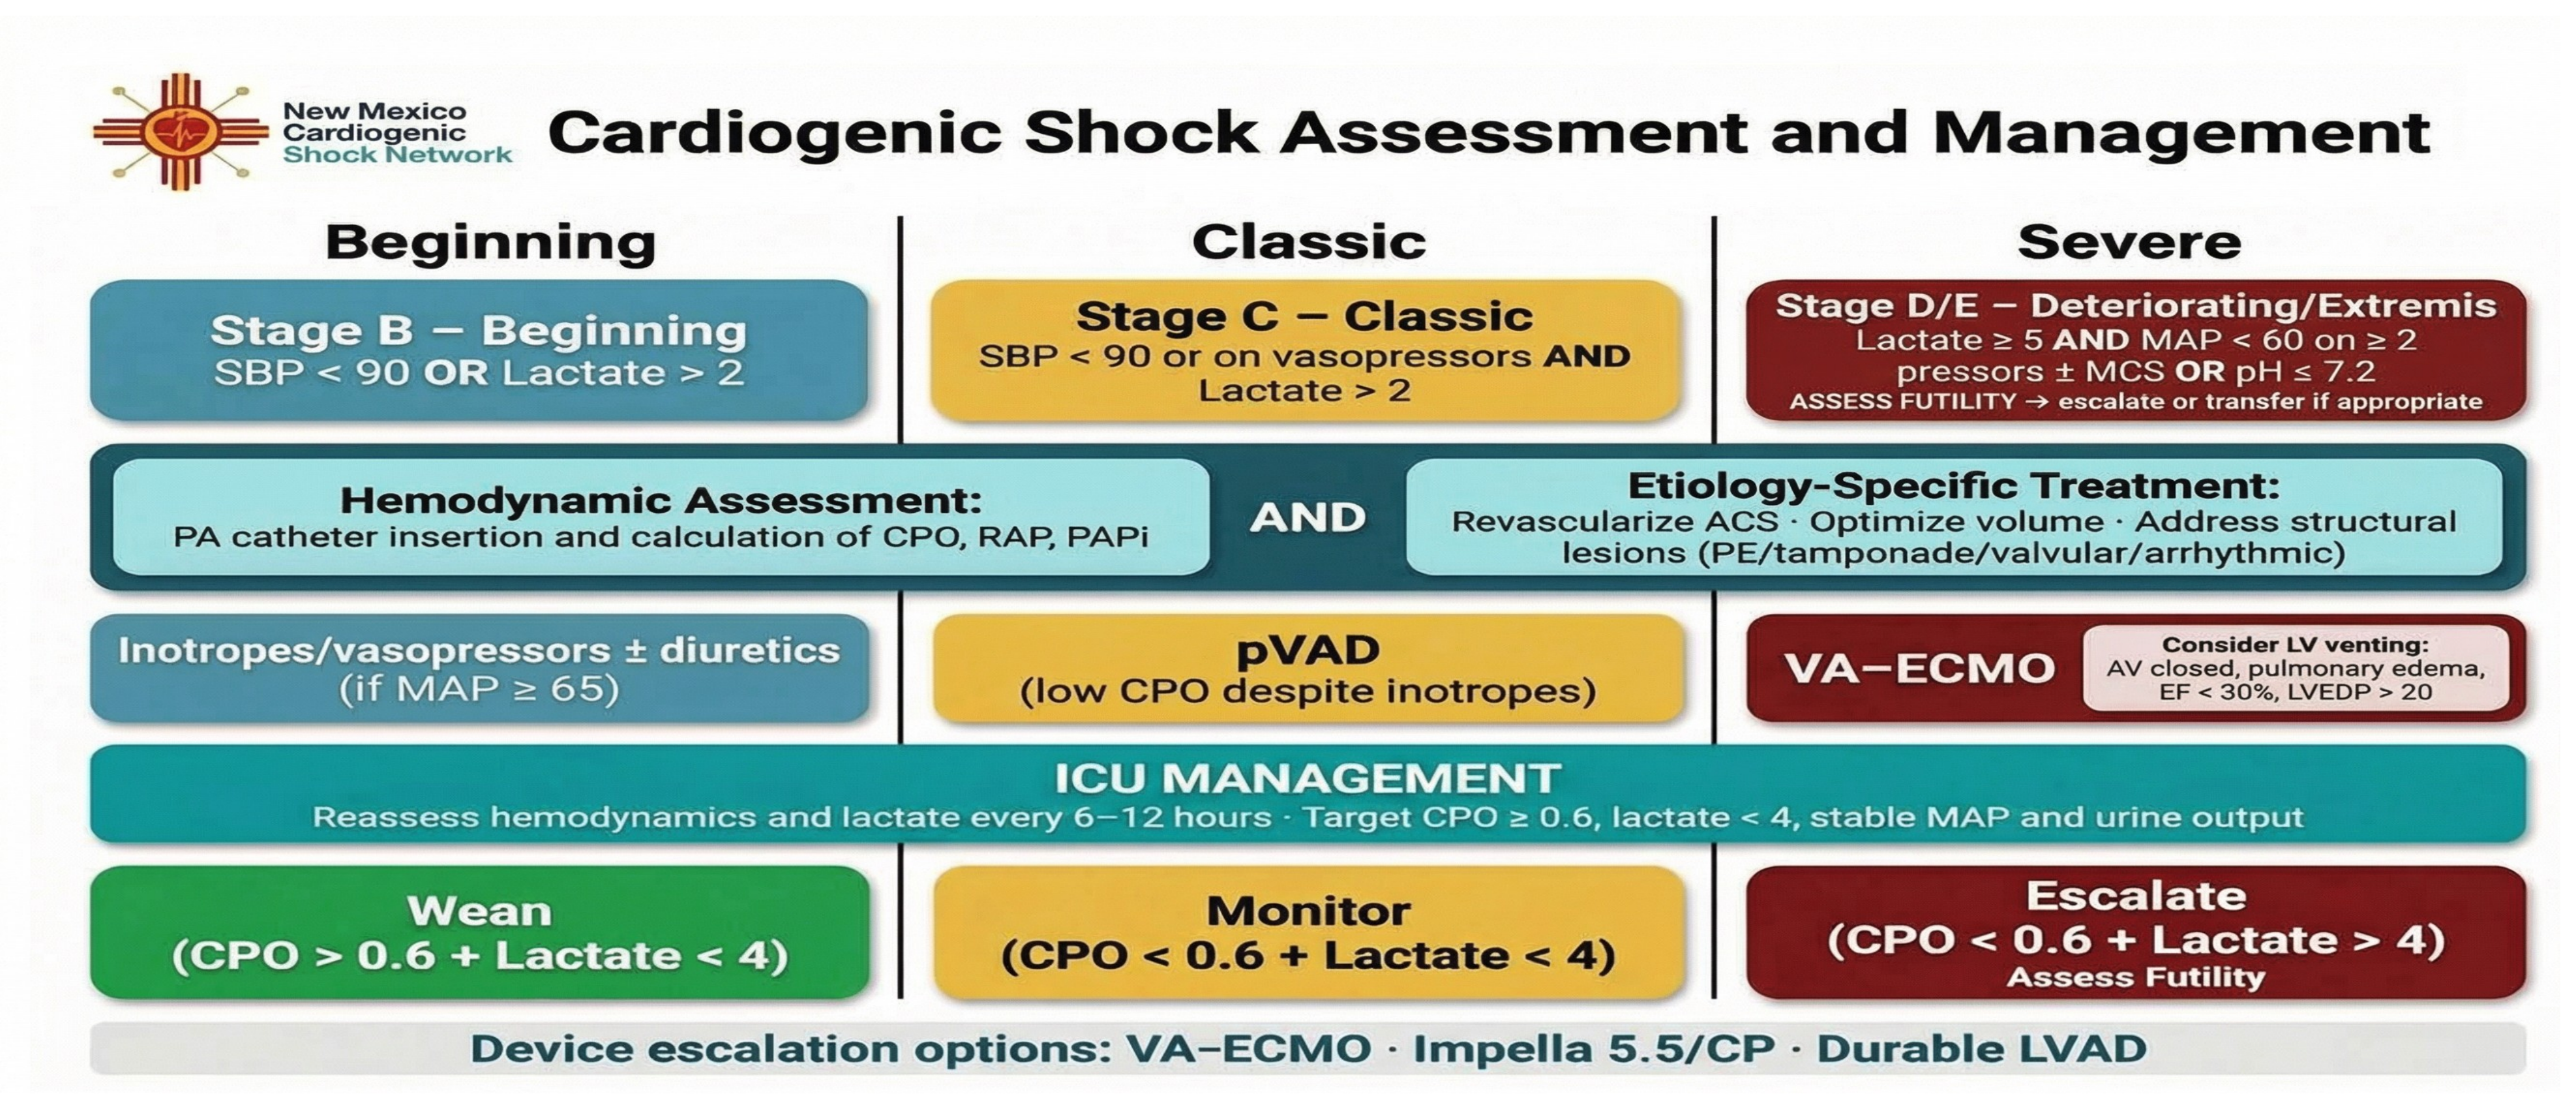
Decision support only. These protocols reflect NMCSN practice and are shared for education and program development; they do not replace your institution's protocols or clinical judgment at the bedside.
Our Results
These results are our own — from a pre/post study of 313 cardiogenic shock patients treated through our program in New Mexico (2019–2024), now published in JSCAI. How the network is structured →
Thirty-day survival rose from 37.6% to 59.4% after the NMCSN hub program launched — our own 313-patient study (p<0.001).
One-year survival rose from 32.7% to 52.4% — the benefit persists long after the initial event.
We receive patients from across New Mexico. The average transfer is about 100 miles.
After implementation, 30-day survival was similar for transferred and directly admitted patients (59.5% vs 59.4%) — with no detected link to transfer distance among patients who reached the hub.
Our Model
One shock network. Every hospital has a role.
New Mexico’s cardiogenic shock capability isn’t distributed evenly — and it doesn’t need to be. What matters is that every hospital knows which role it’s playing today and has the tools to play it well. Heart Hospital of NM is the network’s Level 1 Hub, with a dedicated 24/7 cardiogenic shock program.
The tiers exist to make geography stop mattering. Across our first 313 patients, 30-day survival after implementation was similar whether someone was transferred in or admitted directly — 59.5% against 59.4%, with no detected link to transfer distance among patients who reached the hub. That is a pre/post comparison within one cohort, not a controlled trial, and the study is published in JSCAI. See the results →
Dedicated 24/7 cardiogenic shock program. Full cath lab, every form of temporary mechanical circulatory support including VA-ECMO, and cardiac surgery on site.
Receives transfers. Provides tele-consult. Runs the shock team.
24/7 cath lab, all temporary mechanical circulatory support (IABP, Impella, right-sided support, VA-ECMO) and cardiac surgery on site, without a dedicated 24/7 shock program. Durable LVAD not required.
Revascularizes. Places temporary MCS. Escalates to the hub when needed.
Cath lab, with or without temporary mechanical circulatory support.
Performs initial revascularization. Stabilizes higher-acuity patients. Transfers for advanced support when needed.
No cath lab required.
Recognize cardiogenic shock. Stabilize the patient. Activate the shock network by phone. This is where NMCSN’s staging tool and activation assistant do their work.
Transfers average about 100 miles and reach as far as 320. Survival after implementation did not fall with distance.
A spoke hospital doesn’t need an interventionalist. It needs a staging tool and a phone number.
Transfer line currently routes to Heart Hospital of New Mexico. UNM coming soon.
AI & Innovation
NMCSN is working to bring AI into systems of care — not to replace clinicians, but to extend expertise across geography.
NMCSN is our first case example of a broader vision: AI-enabled, patient-centric systems that can deliver the right expertise, pathways, and logistics to any patient, in any setting. What we build for cardiogenic shock becomes the reusable blueprint for obstetrics, trauma, stroke, and every other time-sensitive condition.
AI-generated education bundles tailored to each audience — ER physicians, ICU teams, EMS, hospital administrators, and legislators.
Real-time decision support for rural EDs using SCAI staging, hemo-metabolic triggers, and transfer algorithms.
REDCap-based multicenter registry with AI-powered quality assurance, outcome tracking, and equity analytics across all network sites.
Machine learning models to predict deterioration, benchmark performance, and optimize resource allocation across the network.
We are actively seeking partnerships with leading AI companies to build the infrastructure for AI-enabled healthcare delivery across rural America.
Explore PartnershipLeadership
Each of us keeps a north star — the vision board we actually navigate by. They are on this page on purpose. This network was built by people who lead from what they believe, and we would rather show you that than tidy it away.

Chief of Advanced Heart Failure & MCS
Heart Hospital of NM (Ardent Health)
Dr. Yau is an interventional and advanced heart failure cardiologist who founded NMCSN on a conviction: where you live should not decide whether you survive cardiogenic shock. He wrote the network’s shock protocols and leads the research behind them — including the 2019–2024 cohort in which 30-day survival rose from 37.6% to 59.4%.
My North Star →
My North Star
Acute Care Nurse Practitioner & Critical Care Expert
MCS Coordinator & POCUS Educator
Robyn is an acute care nurse practitioner and critical care expert. As MCS coordinator and POCUS educator, she trains the bedside clinicians whose ultrasound skills and early recognition the entire activation algorithm depends on.
Open full size →
My North Star
Emergency Medicine Physician
ACEP NM President & EMS Medical Director
Dr. DiDomenico is an emergency medicine physician, President of the New Mexico chapter of ACEP, and an EMS medical director. He represents the network’s front door — the emergency rooms and EMS crews who make the first call.
Open full size →Get In Touch
Whether you run a hospital that wants to join the network, a foundation funding rural health, or you're a clinician with a question about the protocols — we answer every message.
Join as a hub or spoke site, or adopt the protocols at your center.
Email the network →Support rural health equity infrastructure with measurable outcomes.
Request our materials →Questions on the algorithms, or a paper we should be covering.
Ask a question →Every month we publish newly verified cardiogenic shock literature — open to everyone, no account and no subscription needed.
Read this month’s update →Partner With Us
Frontier America deserves frontier medicine. In New Mexico, a small and diverse state, we are building, testing and measuring new ways to care for patients wherever they live. We are seeking partners who share our vision of AI-enabled, patient-centric systems of care. If you care for patients anywhere in New Mexico or the surrounding region, you can use this network today — there is no application, no minimum volume, and no agreement required to make a call.
Call the shock line now — 1-888-727-7646. You do not need a confirmed diagnosis and you do not need an agreement in place. One call reaches the shock team. Not sure it qualifies? Run the activation tool.
Pilot AI tools for clinical decision support, registry analytics, documentation, and education in a real-world network being built statewide.
Every hospital has a role, whatever its cath lab status — see the capability tiers. For most Level 3 centers, joining means adopting the staging tool and the activation number. Formal agreements are being drafted; for now the first step is simply telling us you’re in — email admin@nmcsn.org.
POCUS education, shock recognition, and teaching material for ER, ICU, and EMS teams. Start with Focus on POCUS, or email admin@nmcsn.org to ask what is available.
We are building a prospective multicenter cardiogenic shock registry for New Mexico. Tell us your institution is interested — admin@nmcsn.org.
Fund rural health equity infrastructure with measurable outcomes. NMCSN aligns with state and federal rural health transformation priorities.
NMCSN is a nonprofit organization. Donations fund the work directly — shock protocols built for statewide use, clinician education, and the registry that measures whether more New Mexicans survive. To donate or support the network, email admin@nmcsn.org.
Raymond Yau, MD
Chair, NMCSN
Chief of Advanced Heart Failure & MCS
Heart Hospital of NM
Figures cited from single-arm and before–after studies describe association, not causation. Reference 3 is a national database study, published in Circulation: Heart Failure; reference 4 is our own study, published in JSCAI. Our own outcomes are reported in the Results section above.